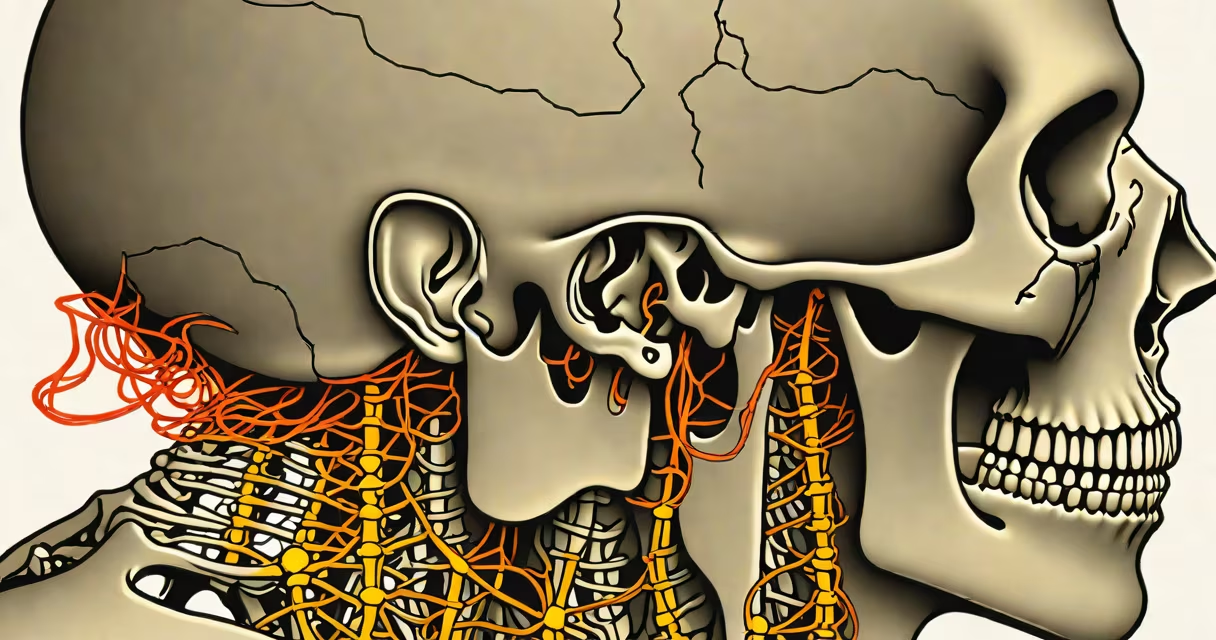
Pain in upper neck lower skull refers to discomfort in the region where the neck meets the base of the skull, typically involving the suboccipital muscles, upper cervical vertebrae, and nerves like the greater occipital nerve. This area is sensitive to posture, stress, and trauma.
This pain often presents as a dull ache, sharp stab, or tight band around the back of the head and upper neck. It may radiate to one side or both sides, worsen with prolonged sitting or screen use, and improve with movement or heat. Common triggers include poor ergonomics, whiplash, or chronic tension from anxiety or sleep position.
The condition is frequently mislabeled as "tension headache" or "neck strain," but accurate diagnosis requires distinguishing between muscular, neurological, and structural causes. For example, occipital neuralgia-a condition where the greater occipital nerve becomes inflamed-can mimic migraine symptoms but responds to specific nerve blocks rather than standard painkillers.
The upper neck and base of the skull house complex structures: the C1 and C2 vertebrae (atlas and axis), the suboccipital triangle muscles (obliquus capitis superior and inferior), and the greater and lesser occipital nerves. These nerves exit the spinal cord near C1-C2 and travel through the neck to supply sensation to the scalp.
When the suboccipital muscles tighten due to sustained forward head posture-common during long hours at a desk-the pressure on these nerves increases. A 2021 study in *The Journal of Orthopaedic & Sports Physical Therapy* found that 68% of patients with chronic upper neck pain had reduced cervical extension range of motion, directly linking posture to symptom onset.
Other triggers include sudden neck movements (like in car accidents), repetitive strain from texting ("text neck"), or sleeping with an overly high pillow. Even dehydration can reduce disc cushioning in the cervical spine, increasing joint stress and contributing to localized pain.
Not all pain in this region is the same. The following table outlines key types, their features, and typical causes:
| Type | Key Features | Common Causes | Diagnostic Clue |
|---|---|---|---|
| Suboccipital muscle strain | Dull, achy pain; worsens with neck rotation | Poor posture, prolonged sitting, stress | Pain localized to one side, improves with massage |
| Occipital neuralgia | Sharp, electric-like shooting pain; often one-sided | Nerve compression, prior injury, diabetes | Positive Tinel's sign at the base of the skull |
| C1-C2 joint dysfunction | Stiffness, limited neck motion, headaches | Whiplash, arthritis, congenital anomalies | Pain worsens with neck flexion or extension |
| Referred pain from TMJ | Deep ache behind ear, jaw tenderness | Bruxism, jaw clenching, arthritis | Pain correlates with jaw movement |
A common error is assuming all upper neck pain is muscular. In reality, nerve entrapment or joint issues may require different treatment. For example, a patient with occipital neuralgia may report pain that feels like a "knife stabbing" at the base of the skull-despite normal MRI results. Diagnosis relies on clinical exam, not imaging alone.
One non-obvious fact: the greater occipital nerve runs close to the posterior arch of C1. If this bone is slightly misaligned-often due to trauma-it can compress the nerve. This is not visible on routine MRI scans but may be detected via physical examination using palpation and range-of-motion testing.
In 2022, a 34-year-old office worker reported persistent pain at the base of her skull, especially after long meetings. She described a "tight band" that worsened when she looked down at her phone. Her primary care provider diagnosed "tension headache" and prescribed ibuprofen, which offered minimal relief.
She later saw a physical therapist who identified restricted C1-C2 motion and tenderness over the greater occipital nerve. After five sessions of manual therapy targeting the suboccipital muscles and joint mobilization, her pain dropped from 7/10 to 2/10 within three weeks. She also learned ergonomic adjustments: raising her monitor to eye level and taking microbreaks every 20 minutes.
This case illustrates that even mild mechanical strain can lead to significant pain when compounded by daily habits. Early intervention prevents progression to chronic pain states.
Not all pain in upper neck lower skull requires a doctor. However, certain red flags demand prompt evaluation. These include:
If you experience any of these, seek care immediately. The American Academy of Neurology notes that cervical spine injuries can lead to permanent neurological damage if missed early.
For ongoing but stable symptoms, start with a physical therapist trained in musculoskeletal conditions. They can assess posture, movement patterns, and muscle imbalances. If symptoms persist beyond four weeks, consider seeing a neurologist or rheumatologist-especially if there's history of autoimmune disease.
Home management includes gentle stretching, such as chin tucks and seated neck rotations. Apply heat for muscle tension or ice for acute flare-ups. Avoid cradling the phone between ear and shoulder.
People often confuse this pain with migraines. But while migraines involve nausea, light sensitivity, and throbbing pain, upper neck lower skull pain is usually constant and tied to movement or posture. Distinguishing between them avoids unnecessary medication use.
Understanding pain in upper neck lower skull begins with recognizing it as a signal-not a flaw. It reflects how the body adapts to stress, posture, and environment. Addressing root causes leads to lasting relief, not temporary fixes.