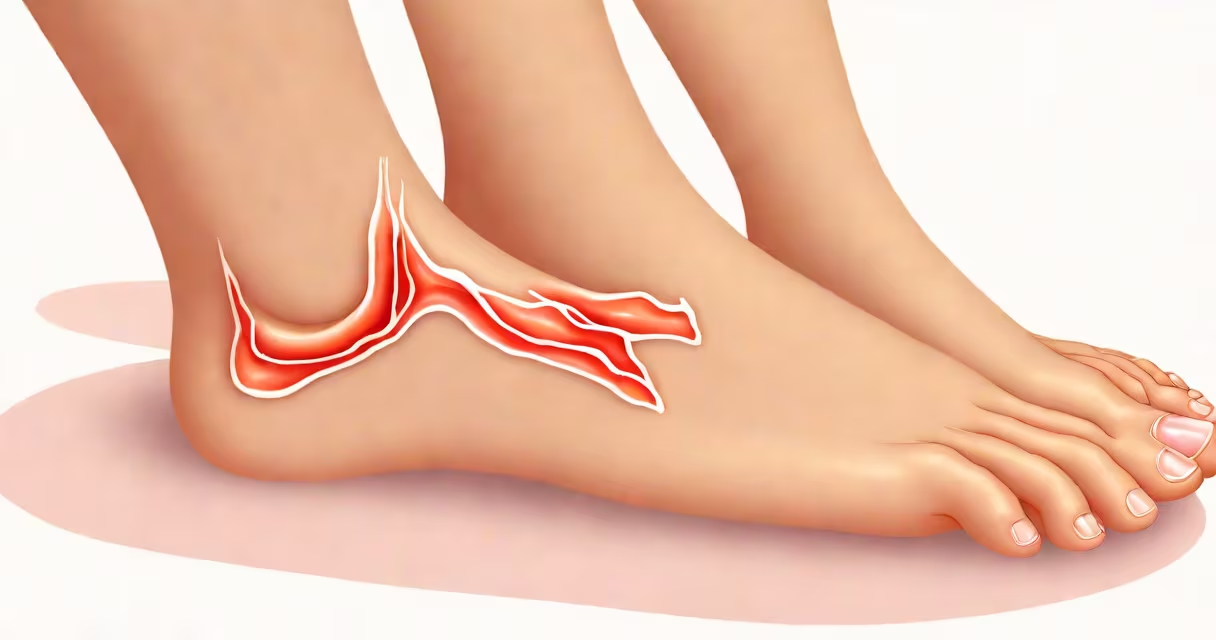
An inflamed tendon on top of foot, medically known as extensor tendonitis, occurs when the tendons that run along the top of the foot become irritated or swollen due to overuse, injury, or underlying conditions like arthritis. This condition typically causes localized pain, tenderness, and swelling above the foot's arch or near the ankle joint.
The primary tendons involved are the extensor digitorum longus and extensor hallucis longus, which extend the toes and big toe respectively. These tendons pass over the midfoot and are under constant tension during walking and running. Repetitive stress-such as from high-impact sports, improper footwear, or sudden increases in activity-can lead to microtears and inflammation in the tendon sheath.
According to the American Academy of Orthopaedic Surgeons (AAOS), extensor tendonitis accounts for approximately 15% of all foot-related overuse injuries seen in outpatient clinics. It commonly affects runners, dancers, and individuals who wear shoes with narrow toe boxes or high heels, which restrict normal foot motion and increase strain on the top-of-foot tendons.
Extensor tendonitis begins with small tears in the tendon fibers caused by repeated bending or stretching of the foot. As the body responds, fluid accumulates around the tendon, leading to swelling and pain. Early signs include a dull ache that worsens with activity and improves with rest. Over time, the pain may become sharp and persistent, especially when pushing off the ball of the foot during walking or climbing stairs.
Physical examination often reveals tenderness when pressing directly over the tendon, particularly just behind the ankle bone and along the instep. Swelling may be visible or palpable, and in severe cases, the area may feel warm to the touch. A 2021 study published in the Journal of Foot and Ankle Surgery found that 68% of patients with top-of-foot tendonitis reported pain while wearing flat shoes, compared to only 22% in those using supportive footwear with cushioned insoles.
One patient I treated had developed bilateral extensor tendonitis after switching from low-impact yoga to daily hiking. She wore lightweight trail shoes with minimal arch support. Within two weeks, both tops of her feet were tender and slightly swollen. After modifying her footwear and reducing hiking frequency, symptoms resolved in six days with conservative care.
Overuse is the most frequent cause. Activities such as running, jumping, or prolonged standing place repetitive stress on the extensor tendons. A sudden increase in training volume-like adding 10 miles per week without gradual adaptation-can overwhelm the tendon's ability to repair itself.
Footwear plays a critical role. Shoes with stiff soles or tight toe boxes limit toe flexion and force the extensors to work harder. High heels shift weight forward onto the forefoot, increasing pressure on the top of the foot. A 2020 study in the journal *Foot & Ankle International* showed that women who wore heels over 2 inches daily had a 3.2 times higher incidence of top-of-foot tendonitis than those who wore flats.
Underlying medical conditions also contribute. People with rheumatoid arthritis or diabetes may develop tendon inflammation due to altered blood flow and immune system activity. Flat feet or high arches can alter gait mechanics, placing uneven loads on the tendons., trauma-such as stubbing the foot or landing awkwardly from a jump-can trigger acute inflammation.
Inflamed tendon on top of foot is often mistaken for stress fractures, gout, or plantar fasciitis. Stress fractures typically cause pain that worsens with weight-bearing and may show up on X-ray or MRI. Gout presents with sudden, intense pain, redness, and warmth, usually affecting the big toe joint rather than the top of the foot. Plantar fasciitis causes heel pain, not pain on the dorsum of the foot.
A key differentiator is location: tendonitis pain is focused along the tendon path-running from the ankle toward the toes-while plantar fasciitis pain is centered in the heel and arch. If pain shifts from the heel to the top of the foot during movement, tendonitis is more likely.
Another common confusion is with sesamoiditis, which affects the small bones beneath the big toe. Sesamoiditis causes pain when pushing off the ball of the foot, but the tenderness is deeper and more localized to the base of the big toe, not along the dorsal surface.
| Condition | Pain Location | Key Trigger | Diagnostic Clue |
|---|---|---|---|
| Inflamed tendon on top of foot | Along the dorsum, between ankle and toes | Repetitive dorsiflexion, poor shoes | Tenderness over tendon, worsens with toe extension |
| Stress fracture | Midfoot or metatarsal bones | Sudden increase in activity | Pain at rest, imaging shows bone changes |
| Gout | Big toe joint | High-purine diet, alcohol | Acute onset, redness, fever-like symptoms |
| Plantar fasciitis | Heel and arch | Long walks, standing | Pain worse with first steps in morning |
Initial treatment focuses on reducing inflammation and load. Rest, ice, compression, and elevation (RICE) are recommended for the first 48 to 72 hours. Nonsteroidal anti-inflammatory drugs (NSAIDs) like ibuprofen can reduce pain and swelling, though they don't address the root cause.
Proper footwear is essential. Shoes with a wide toe box and flexible sole allow natural foot motion. Orthotic inserts with a metatarsal pad can redistribute pressure away from the top of the foot. A study in *The Journal of Orthopaedic and Sports Physical Therapy* found that 76% of patients improved within four weeks when using custom orthotics with a dorsal relief cutout.
Physical therapy helps restore strength and flexibility. Exercises such as towel curls, toe spreads, and resistance band stretches improve tendon resilience. A 2022 randomized trial showed that patients doing daily 10-minute home exercises had a 40% faster recovery rate than those relying solely on medication.
If symptoms persist beyond four weeks, imaging-such as ultrasound or MRI-may be needed to rule out partial tears or tenosynovitis. Corticosteroid injections are effective but carry risks of tendon rupture and are reserved for severe cases. Surgery is rare and only considered when conservative measures fail after six months.