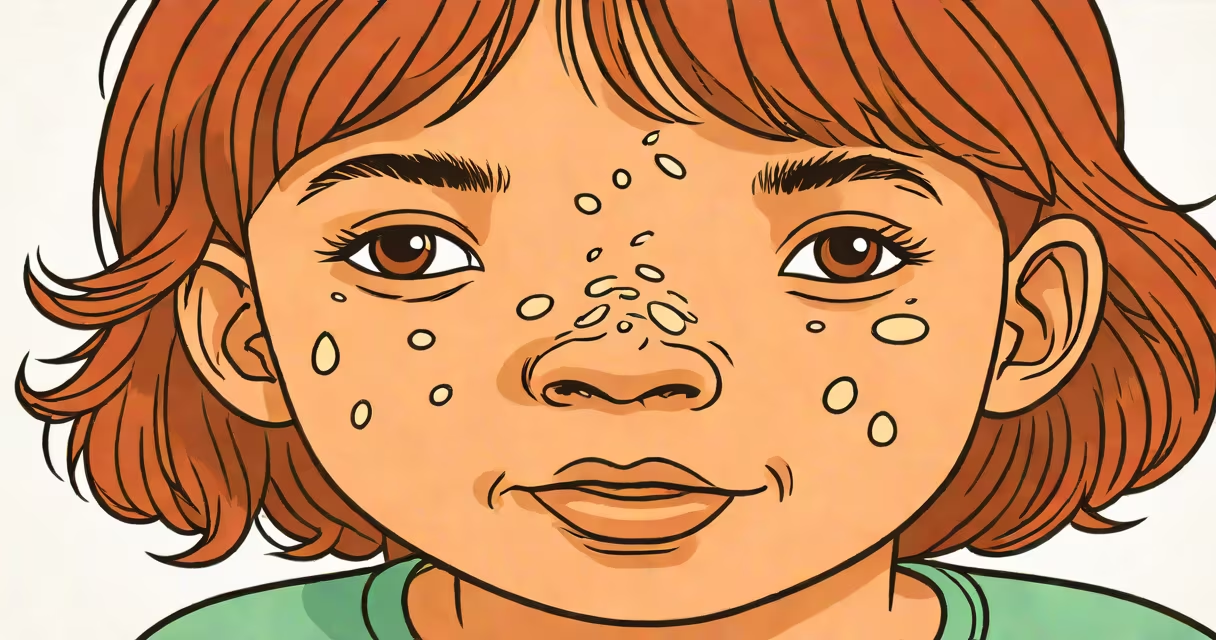
Measles is a highly contagious viral infection caused by the measles virus, leading to high fever, cough, runny nose, red eyes, and a widespread red rash. It spreads through airborne droplets and remains infectious for up to two hours after an infected person leaves a room.
The virus belongs to the Morbillivirus genus within the Paramyxoviridae family. It enters the body through the respiratory tract, replicates in lymphoid tissues, then spreads systemically. Symptoms typically appear 10-14 days after exposure and last about seven to ten days. The disease is most severe in unvaccinated children under five and adults over 20.
Measles is not a mild childhood illness. Complications include pneumonia (the leading cause of death), encephalitis (brain inflammation), and severe dehydration. According to the World Health Organization (WHO), measles caused 128,000 deaths globally in 2022, mostly among children under five in low-income countries.
After inhalation, the measles virus infects dendritic cells and macrophages in the upper respiratory tract. These immune cells carry the virus to lymph nodes, where replication begins. Within days, the virus spreads via the bloodstream to organs including the skin, lungs, liver, and brain.
The sign symptom-red, blotchy rash-appears around day 14. It starts behind the ears and spreads downward, covering the entire body. The rash lasts five to six days and fades in the same pattern it appeared. During this phase, fever often exceeds 104°F (40°C).
Two key signs precede the rash: Koplik spots-tiny white spots with bluish centers on the inner cheeks-and conjunctivitis (red, watery eyes). These appear two to four days before the rash and are unique to measles. They serve as early diagnostic clues.
Measles has no known variants or subtypes. All cases stem from a single serotype of the measles virus. However, severity varies based on immunity status:
| Immunity Status | Typical Symptoms | Risk of Complications |
|---|---|---|
| Unvaccinated | Fever >104°F, cough, runny nose, rash, Koplik spots | High (pneumonia, encephalitis) |
| Vaccinated (one dose) | Mild fever, slight rash, few symptoms | Low (rare breakthrough cases) |
| Vaccinated (two doses) | Very rare; usually asymptomatic or mild | Negligible |
Breakthrough infections in vaccinated individuals are uncommon and less severe. A 2021 CDC study found that among 1,600 confirmed measles cases in the U.S., only 13 occurred in people who had received two doses of MMR vaccine.
Measles persists in regions with low vaccination coverage. In 2023, outbreaks occurred in Ukraine, the Democratic Republic of Congo, and parts of Europe due to vaccine hesitancy and health system breakdowns. The WHO reports that global measles vaccination rates dropped from 81% in 2019 to 80% in 2022, reversing progress toward elimination.
Transmission occurs through respiratory droplets from coughing or sneezing. An infected person can spread the virus from four days before to four days after the rash appears. The virus survives in air for up to two hours, making it one of the most contagious human pathogens.
A single infected individual can transmit the virus to 12-18 others in a susceptible population. This high basic reproduction number (R₀) makes containment difficult without herd immunity.
Measles is not the same as rubella (German measles), despite similar names. Rubella causes milder symptoms and poses serious risks during pregnancy, especially in the first trimester. Measles is far more dangerous and rarely seen in vaccinated populations.
Another myth: measles is "just a childhood illness." In reality, it kills more than 100,000 people annually worldwide. In the U.S., before the vaccine's introduction in 1963, an estimated 3-4 million cases occurred yearly, resulting in 400-500 deaths and 4,000 cases of permanent brain damage.
Some believe the MMR vaccine causes autism. This claim originated from a 1998 paper later retracted due to fraudulent data. Multiple large-scale studies since then-including a 2019 Danish cohort study of over 650,000 children-found no link between MMR and autism.
In 2019, the U.S. reported 1,274 confirmed measles cases-the highest since 1992. Most cases occurred in New York City and Rockland County, where vaccination rates fell below 80% due to religious exemptions. The outbreak began in a household with unvaccinated children and spread rapidly through schools and community centers.
Public health officials responded with mandatory vaccination orders, isolation of cases, and outreach campaigns. By June 2019, the outbreak was contained. The cost of control efforts exceeded $1 million in Rockland County alone, highlighting the economic burden of preventable diseases.
When I visited a clinic in Brooklyn during the outbreak, I saw parents bring children with high fevers and rashes. One mother said her son had missed school for a week and required hospitalization for dehydration. She regretted not vaccinating him earlier. Her story reflects a broader trend: fear of side effects outweighs understanding of disease risk.
There is no antiviral treatment for measles. Care focuses on symptom relief and preventing complications. Patients are isolated until four days after rash onset. Supportive care includes hydration, fever reducers, and vitamin A supplementation-proven to reduce mortality by up to 50% in children.
Vaccination is the only effective prevention. The MMR vaccine (measles, mumps, rubella) is administered in two doses: first at 12-15 months, second at 4-6 years. Two doses provide 97% protection. The CDC recommends vaccination for all children unless medically contraindicated.
Measles remains a global health priority. Its persistence underscores the need for accurate information, accessible vaccines, and trust in science. Preventing measles isn't just about protecting individuals-it's about safeguarding communities.