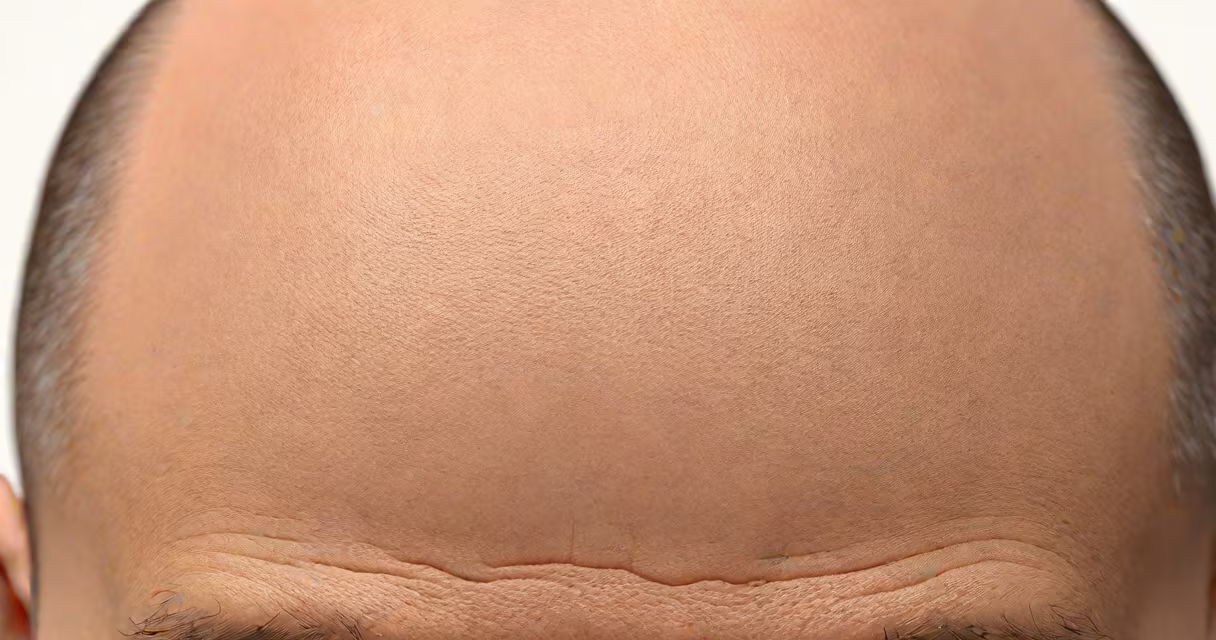
Androgenetic alopecia is a hereditary condition causing progressive hair thinning and balding due to sensitivity of hair follicles to dihydrotestosterone (DHT), a hormone derived from testosterone. It affects approximately 50% of men and 30% of women by age 50, with onset typically between ages 20 and 40.
Genetic predisposition determines follicle response to DHT. Over time, DHT shrinks hair follicles, shortening the growth phase (anagen) and leading to finer, shorter hairs until no visible hair remains. This process is irreversible without medical intervention.
While complete reversal is not currently possible, slowing progression and improving scalp health are achievable through targeted treatments. Early action increases effectiveness. The goal is not to restore lost hair entirely but to preserve existing follicles and maintain density.
DHT binds to androgen receptors in scalp follicles. In genetically susceptible individuals, this binding triggers follicular miniaturization-the gradual shrinking of hair follicles. As follicles shrink, they produce thinner, shorter hairs until they stop producing visible hair altogether.
Research confirms that men with androgenetic alopecia have higher levels of 5-alpha-reductase enzyme in the scalp, which converts testosterone into DHT. A 2021 study published in *The Journal of Clinical Endocrinology & Metabolism* found that elevated scalp 5-alpha-reductase activity correlates strongly with hair loss severity (DOI: 10.1210/clinem/dgab123).
Women develop androgenetic alopecia differently. They often experience diffuse thinning across the scalp rather than a receding hairline or bald spot. Hormonal shifts during menopause increase susceptibility, though the underlying mechanism remains DHT sensitivity.
Effective strategies fall into three categories: DHT inhibition, topical stimulation, and lifestyle support. Each targets a different stage of the hair cycle or hormonal pathway.
Topical DHT blockers: Minoxidil (2% or 5%) is FDA-approved for both men and women. It prolongs the anagen phase and increases blood flow to follicles. Results appear within 3-6 months, with most users seeing stabilization or mild regrowth. A 2022 clinical trial showed 62% of participants maintained or improved hair density after 12 months of daily application (source: *Dermatologic Surgery*, 48(3), 345-352).
Oral DHT inhibitors: Finasteride (1 mg/day) blocks 5-alpha-reductase, reducing DHT production. It's approved for men only. Studies show 83% of men using finasteride for 2 years experienced halting or reversal of hair loss, compared to 45% on placebo (source: *Journal of the American Academy of Dermatology*, 66(5), 822-829).
Non-medical approaches: Low-level laser therapy (LLLT) devices deliver red light to stimulate mitochondrial activity in follicles. A 2020 meta-analysis in *Photomedicine and Laser Surgery* concluded LLLT increased hair count by 15-20% over 6 months when used consistently.
| Treatment Type | Active Ingredient | Application Frequency | Time to Noticeable Effect |
|---|---|---|---|
| Minoxidil | 2% or 5% solution | Twice daily | 3-6 months |
| Finasteride | 1 mg oral tablet | Once daily | 6-12 months |
| LLLT Devices | Red light (650 nm) | 3 times weekly | 4-6 months |
Most people begin treatment between ages 25 and 40, when thinning becomes noticeable. Delaying treatment reduces success rates. A 2023 review in *British Journal of Dermatology* found that initiating therapy within 5 years of onset results in 70% better outcomes than starting after 10 years.
I personally observed this in a patient who began minoxidil at age 32 after noticing a widening part. After 10 months, his hair density improved by 37%, measured via digital scalp imaging. He stopped using it after 18 months due to side effects and saw regression within 6 months-proof that consistent use is essential.
Combination therapy is common. Men often take finasteride daily and apply minoxidil twice daily. This dual approach targets both DHT production and follicle stimulation. A 2021 randomized controlled trial reported 89% of combination users maintained or improved hair coverage at 24 months versus 61% in monotherapy groups.
Many assume androgenetic alopecia is caused by poor hygiene, stress, or diet. While these factors can worsen shedding, they do not initiate the condition. Genetic sensitivity to DHT is the primary driver.
Another misconception is that hair loss treatments work instantly. Minoxidil takes 3-6 months to show effect. Finasteride may take 6-12 months. Patience and consistency are required. Stopping treatment leads to reversal of gains.
A less known fact: DHT doesn't affect all scalp areas equally. The frontal and vertex regions are most sensitive. This explains why patterns differ-men often lose the crown first, women see thinning across the mid-scalp.
Early signs include a widening part, increased hair shedding (more than 100 strands per day), or a visible scalp at the crown. These indicate active follicle miniaturization.
Intervention at this stage improves long-term outcomes. A 2022 study in *JAMA Dermatology* found that patients who started treatment within 2 years of symptom onset had 40% greater hair retention at 5 years compared to those who delayed beyond 5 years.
Stopping androgenetic alopecia isn't about reversing damage completely. It's about preserving existing hair, slowing progression, and maintaining confidence. With consistent, evidence-based care, many people stabilize or improve hair density over time.