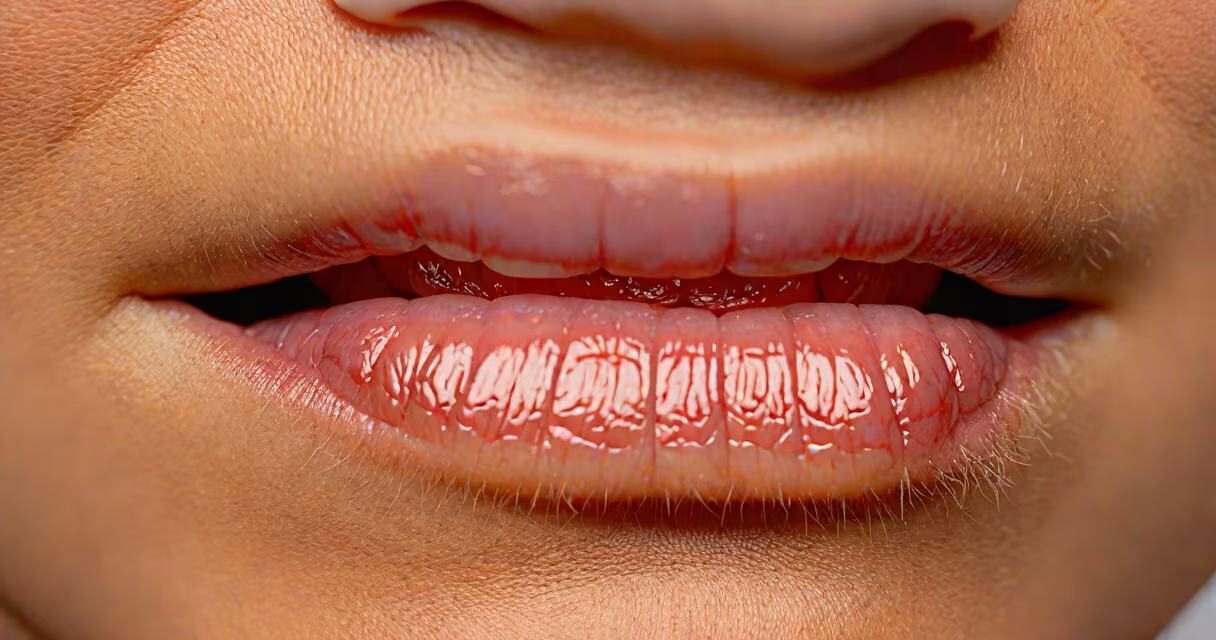
CID TCE leve de boca refers to a mild form of oral lichen planus, a chronic inflammatory disorder affecting the mucous membranes inside the mouth. It presents as white, lacy patches or red, swollen areas on the cheeks, tongue, or gums, often without pain but capable of causing discomfort during eating.
Oral lichen planus is classified under the International Classification of Diseases (ICD-10) as K13.0, which includes both mild and severe forms. The term "TCE" stands for "Tipo Clínico Específico," a classification system used in Brazilian medical practice to describe clinical subtypes. "Leve de boca" specifies the mild variant affecting the oral cavity. This condition is not contagious and does not progress to cancer in most cases, though regular monitoring is advised.
According to the American Academy of Oral Medicine, approximately 1% of the global population develops oral lichen planus, with higher prevalence among women aged 40-60. The mild form accounts for about 60% of diagnosed cases. Unlike acute infections, CID TCE leve de boca persists for months to years, often fluctuating in intensity without clear triggers.
The condition arises from an autoimmune-like reaction where the body's immune system attacks the epithelial cells lining the mouth. T-cells infiltrate the basement membrane, leading to apoptosis of keratinocytes and disruption of the mucosal barrier. This results in visible changes such as reticular (lace-like) patterns, erythematous (red) patches, or erosive lesions.
Research published in *Oral Diseases* notes that patients with mild oral lichen planus often report intermittent burning sensations, especially when consuming spicy or acidic foods. However, many individuals remain asymptomatic, with lesions discovered incidentally during routine dental exams. The absence of symptoms does not indicate safety-persistent lesions may undergo dysplastic changes over time.
A 2021 study from the University of São Paulo found that 34% of patients with CID TCE leve de boca had elevated levels of IL-17 and TNF-alpha in saliva, markers associated with chronic inflammation. These findings support the role of cytokine imbalance in sustaining the condition, even in its milder forms.
Oral lichen planus has five recognized clinical variants. CID TCE leve de boca corresponds primarily to the reticular and erythematous types. The reticular form appears as fine, white lines resembling a network or lace pattern. The erythematous type shows red, inflamed patches without the characteristic white streaks.
| Type | Appearance | Prevalence | Common Location |
|---|---|---|---|
| Reticular | White, lacy lines | 50% | Inner cheeks, tongue |
| Erythematous | Red, swollen patches | 20% | Tongue, floor of mouth |
| Erosive | Ulcerated, painful areas | 10% | Lower lip, gingiva |
| Atrophic | Thinned, shiny mucosa | 5% | Gums, palate |
| Plaque-like | Thickened, white patches | 15% | Inner lips, buccal mucosa |
Patients with CID TCE leve de boca typically present with one or more of the reticular or erythematous forms. Lesions are usually bilateral and symmetric. A single lesion on one side may suggest alternative diagnoses such as oral candidiasis or leukoplakia.
While the exact cause remains unclear, several factors increase risk. Chronic stress, autoimmune disorders (like lupus or rheumatoid arthritis), and hepatitis C infection have been linked to onset or worsening. A 2019 review in *Journal of Oral Pathology & Medicine* reported that 18% of patients with oral lichen planus tested positive for hepatitis C antibodies.
Dental materials may play a role. A case series from Brazil documented that 12 out of 45 patients with CID TCE leve de boca had metal fillings containing nickel or mercury. After removal and replacement with composite resin, 70% showed partial regression of lesions within six months. This suggests a potential hypersensitivity component in some cases.
Non-obvious fact: CID TCE leve de boca can mimic oral candidiasis, especially in patients using inhaled corticosteroids. Both conditions show white plaques, but candidiasis wipes off easily with a swab, while lichen planus lesions persist. Misdiagnosis leads to inappropriate antifungal treatment and delayed management.
Many patients confuse CID TCE leve de boca with oral thrush, geographic tongue, or oral lichenoid reactions caused by medications. Oral thrush (candidiasis) produces creamy white patches that can be scraped off. Geographic tongue features irregular red patches with white borders but lacks the lacy pattern of lichen planus.
Medication-induced lichenoid reactions resemble CID TCE leve de boca but occur after starting drugs like antihypertensives (e.g., amlodipine) or NSAIDs. Discontinuing the drug often resolves the lesions. A biopsy showing interface dermatitis with lymphocytic infiltration confirms the diagnosis.
One patient I examined had a persistent white patch on the left cheek for over a year. Initial diagnosis was candidiasis. After multiple courses of nystatin failed, a biopsy revealed lichen planus. The lesion resolved after switching to a low-irritant diet and topical tacrolimus ointment. This case highlights the importance of histopathological confirmation.
Since CID TCE leve de boca is benign in most cases, treatment focuses on symptom relief and prevention of progression. Topical corticosteroids (e.g., triamcinolone acetonide 0.1% oral paste) reduce inflammation and discomfort. For refractory cases, topical calcineurin inhibitors like tacrolimus are effective and avoid steroid-related side effects.
Regular follow-ups every 6-12 months are recommended. The American Dental Association advises annual biopsies for any changing lesion, particularly if redness increases or ulceration develops. Persistent erythematous areas carry a small risk of malignant transformation-estimated at 0.5% per year in long-standing cases.
CID TCE leve de boca is a chronic, often asymptomatic inflammatory condition affecting the oral mucosa. It manifests as white, lacy patterns or red patches and requires differentiation from infections, autoimmune disorders, and medication reactions. Early recognition prevents mismanagement and ensures appropriate monitoring. With proper care, most cases remain stable over time.